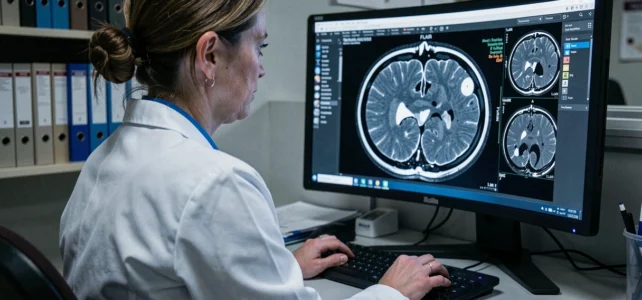
An isolated FLAIR hypersignal does not constitute a diagnosis. The FLAIR sequence (Fluid-Attenuated Inversion Recovery) suppresses the signal from normal cerebrospinal fluid while preserving that of tissue abnormalities, making it very sensitive but not very specific. The significance of a hypersignal in white matter ranges from benign vascular aging to active multiple sclerosis or infiltrating glioblastoma.
The distinction relies on a set of topographic, morphological, and clinical criteria that we detail here.
Lesional Topography in FLAIR: The Underestimated Discriminating Criterion
The location of a FLAIR hypersignal directs the diagnosis more reliably than its intensity or size. A punctate hypersignal in deep white matter, without contact with the ventricular wall, corresponds in the vast majority of cases to microvascular leukoaraiosis, especially in a patient over fifty with known cardiovascular risk factors.
In contrast, a tangle of lesions in contact with the ventricles now constitutes a marker of significant brain pathology, even in the absence of a very high overall lesion volume. This periventricular pattern is characteristic of multiple sclerosis, but also of certain central nervous system vasculitides or neurosarcoidosis.
Juxtacortical lesions (in contact with the cortical ribbon) and lesions of the corpus callosum deserve special attention. A FLAIR hypersignal of the corpus callosum in sagittal orientation, perpendicular to the ventricular axis, strongly suggests a demyelination plaque. An in-depth article discusses FLAIR hypersignals on Geek Medical with a complementary angle on the benign/malignant distinction.
Brainstem lesions in FLAIR present a different problem. A single hypersignal in the pons or medulla, in a young patient, necessitates ruling out a diffuse low-grade glioma or an IDH-wildtype glioblastoma, whose infiltration may remain subtle on initial acquisitions.
Fazekas Score in Brain MRI: Utility and Diagnostic Limits
The Fazekas score remains the most commonly used descriptive tool for grading white matter hypersignals. A Fazekas 1 is common and often benign, corresponding to small scattered punctate foci. A Fazekas 2 (early confluent lesions) or a Fazekas 3 (large periventricular confluence) indicates a heavier lesion burden.
We recommend never interpreting the Fazekas score in isolation. Recent guidelines emphasize a point that reports often overlook: a descriptive score does not equate to an individual prognostic judgment. A Fazekas 2 in a forty-year-old patient without hypertension does not have the same significance as a Fazekas 2 in a seventy-five-year-old patient who has been diabetic and hypertensive for decades.
Integrating the score with other markers of cerebral microangiopathy radically changes the interpretation:
- Presence of associated lacunes on T1 or T2 sequences, indicating old lacunar infarcts and reinforcing the vascular hypothesis
- Micro-hemorrhages visible on susceptibility-weighted imaging (SWI/T2*), suggesting amyloid angiopathy if they predominate in cortical areas, or hypertensive microangiopathy if they are deep
- Dilation of perivascular spaces (Virchow-Robin), common and benign when moderate, but significant when massive and associated with other markers
A Fazekas 3 associated with multiple lacunes and deep micro-hemorrhages constitutes a picture of severe cerebral microangiopathy with an increased risk of stroke and cognitive decline. The same Fazekas 3 without any other associated markers calls for a different etiological exploration.
Morphology and Contrast Enhancement: Alarm Signals in FLAIR Sequence
The shape of a FLAIR hypersignal provides information that the Fazekas score does not capture. A round, well-defined, small, and stable lesion over time is almost always benign. A lesion with indistinct borders, infiltrating, crossing anatomical boundaries (from white matter to gray matter, crossing the midline) should raise suspicion of a tumoral process.
The injection of gadolinium transforms the analysis. A FLAIR hypersignal that does not take up contrast may be old, scar tissue, or correspond to an unenhanced low-grade glioma. An annular enhancement at the periphery suggests a glioblastoma or a cerebral abscess, two therapeutic emergencies that should not be confused.
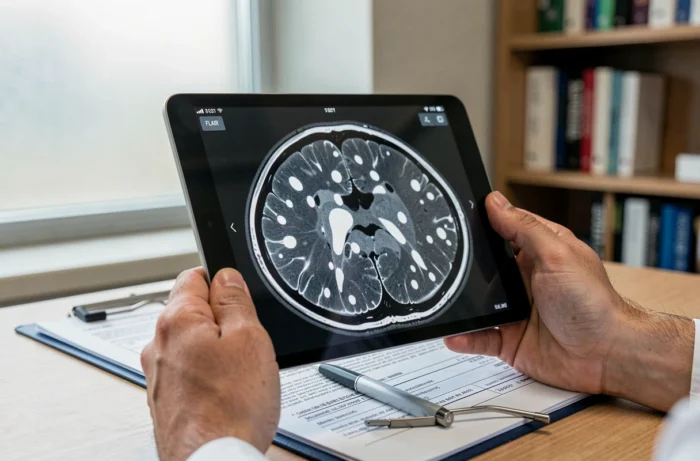
In the context of multiple sclerosis, the contrast enhancement of a FLAIR plaque indicates recent inflammatory activity, which directly modifies the therapeutic strategy. A plaque without enhancement is considered inactive.
Morphological Criteria Indicating a Serious Lesion
- Mass effect on adjacent structures (midline deviation, ventricular compression), absent in benign vascular lesions
- Diffusion restriction on DWI/ADC sequence, suggestive of a recent stroke or pyogenic abscess
- Documented progression on two successive MRIs, whether it is an increase in size or the appearance of new lesions
- Intra-lesional hemorrhagic component visible on T2*, common in high-grade tumors
Follow-up MRI Strategy According to FLAIR Hypersignal Profile
The frequency of imaging surveillance directly depends on the identified lesion profile. Mild hypersignals of Fazekas 1 type, consistent with age and well-controlled vascular factors, generally do not justify systematic re-MRI. Controlling cardiovascular risk factors takes precedence over repeating examinations.
Moderate to severe hypersignals (Fazekas 2 or 3), rapidly progressing lesions, or atypical morphologies require close monitoring. We recommend a follow-up MRI at three or six months to document the evolution, with identical sequences to the initial assessment to allow for reliable comparison.
The most common pitfall remains incidental findings. An isolated FLAIR hypersignal on an MRI performed for benign headaches generates disproportionate anxiety. The clinico-radiological correlation remains the cornerstone of any interpretation: a FLAIR hypersignal without concordant symptoms does not warrant treatment, but may justify monitoring appropriate to the patient’s context.